Speaking during the company’s second-quarter earnings call, Soi attributed the drop to revisions in CGHS rates.
from Top Health News | Latest Healthcare Sector & Healthcare Industry news, Information and Updates: ET HealthWorld : ETHealthworld.com https://ift.tt/Ov6KsCJ
TAKOMA PARK, Md. — Friday night lights took on a whole new meaning at a high school here in this suburb of Washington, D.C.
Instead of fans packing stadium bleachers to watch football, on this recent October weekend the gymnasium, hallways, and parking areas were jammed with people desperately seeking healthcare at a free pop-up clinic.
The 2026 election season has been punctuated by affordability issues, with polls showing high healthcare costs are a top concern among likely voters. The staggering toll of people struggling to get care was on full display here just eight miles northeast of the U.S. Capitol — in an area where census data shows the median household income tops $108,000 and about 94% have health insurance.
Dozens of people slept in their cars overnight outside Takoma Academy to secure spots for free health, dental, or vision care, according to clinic coordinators and interviews with patients.
Though clinic doors were scheduled to open at 6 a.m. Oct. 17, the first patients drove up shortly before midnight. By 4 a.m., three hours before sunrise, about 80 cars had arrived. Patients were given numbers representing their place in line when they entered the parking lot, and they had to be on site when they were notified by text message that it was their turn.
(Eric Harkleroad/KFF Health News)
Kenys Bautista arrived at the school before midnight after driving 20 minutes from her home in Wheaton, Maryland. She wanted to be sure she got the medical and dental checkups that she had put off for three years because she didn’t have insurance or the money to cover the costs.
“It’s really sad that a lot of people like me had to sleep in their car just to see a doctor or dentist because we do not have health insurance,” Bautista said. She works as a payroll specialist for a small company but does not get any health benefits.
Bautista was one of 467 patients at the weekend clinic. Most received dental and/or medical care. Ninety-nine got vision exams, and many left with new eyeglasses, according to clinic organizers.
While most patients at the clinic were uninsured, 1 in 4 had health coverage, such as through Medicare or their employer. But many said just having coverage was not enough, because it left them with unaffordable out-of-pocket costs .
“I never thought I would need a clinic like this, but it’s gotten so expensive in the world,” Alma Walton said. She has Medicare, but routine dental care is not a standard benefit.
Walton, who lives in Camp Springs, Maryland, was 59th in line for care. She arrived around 1:30 a.m. “I wanted to make sure I could get in,” she said. She went to the clinic in hopes of getting a filling fixed after it cracked over the summer. She had postponed seeing a dentist.
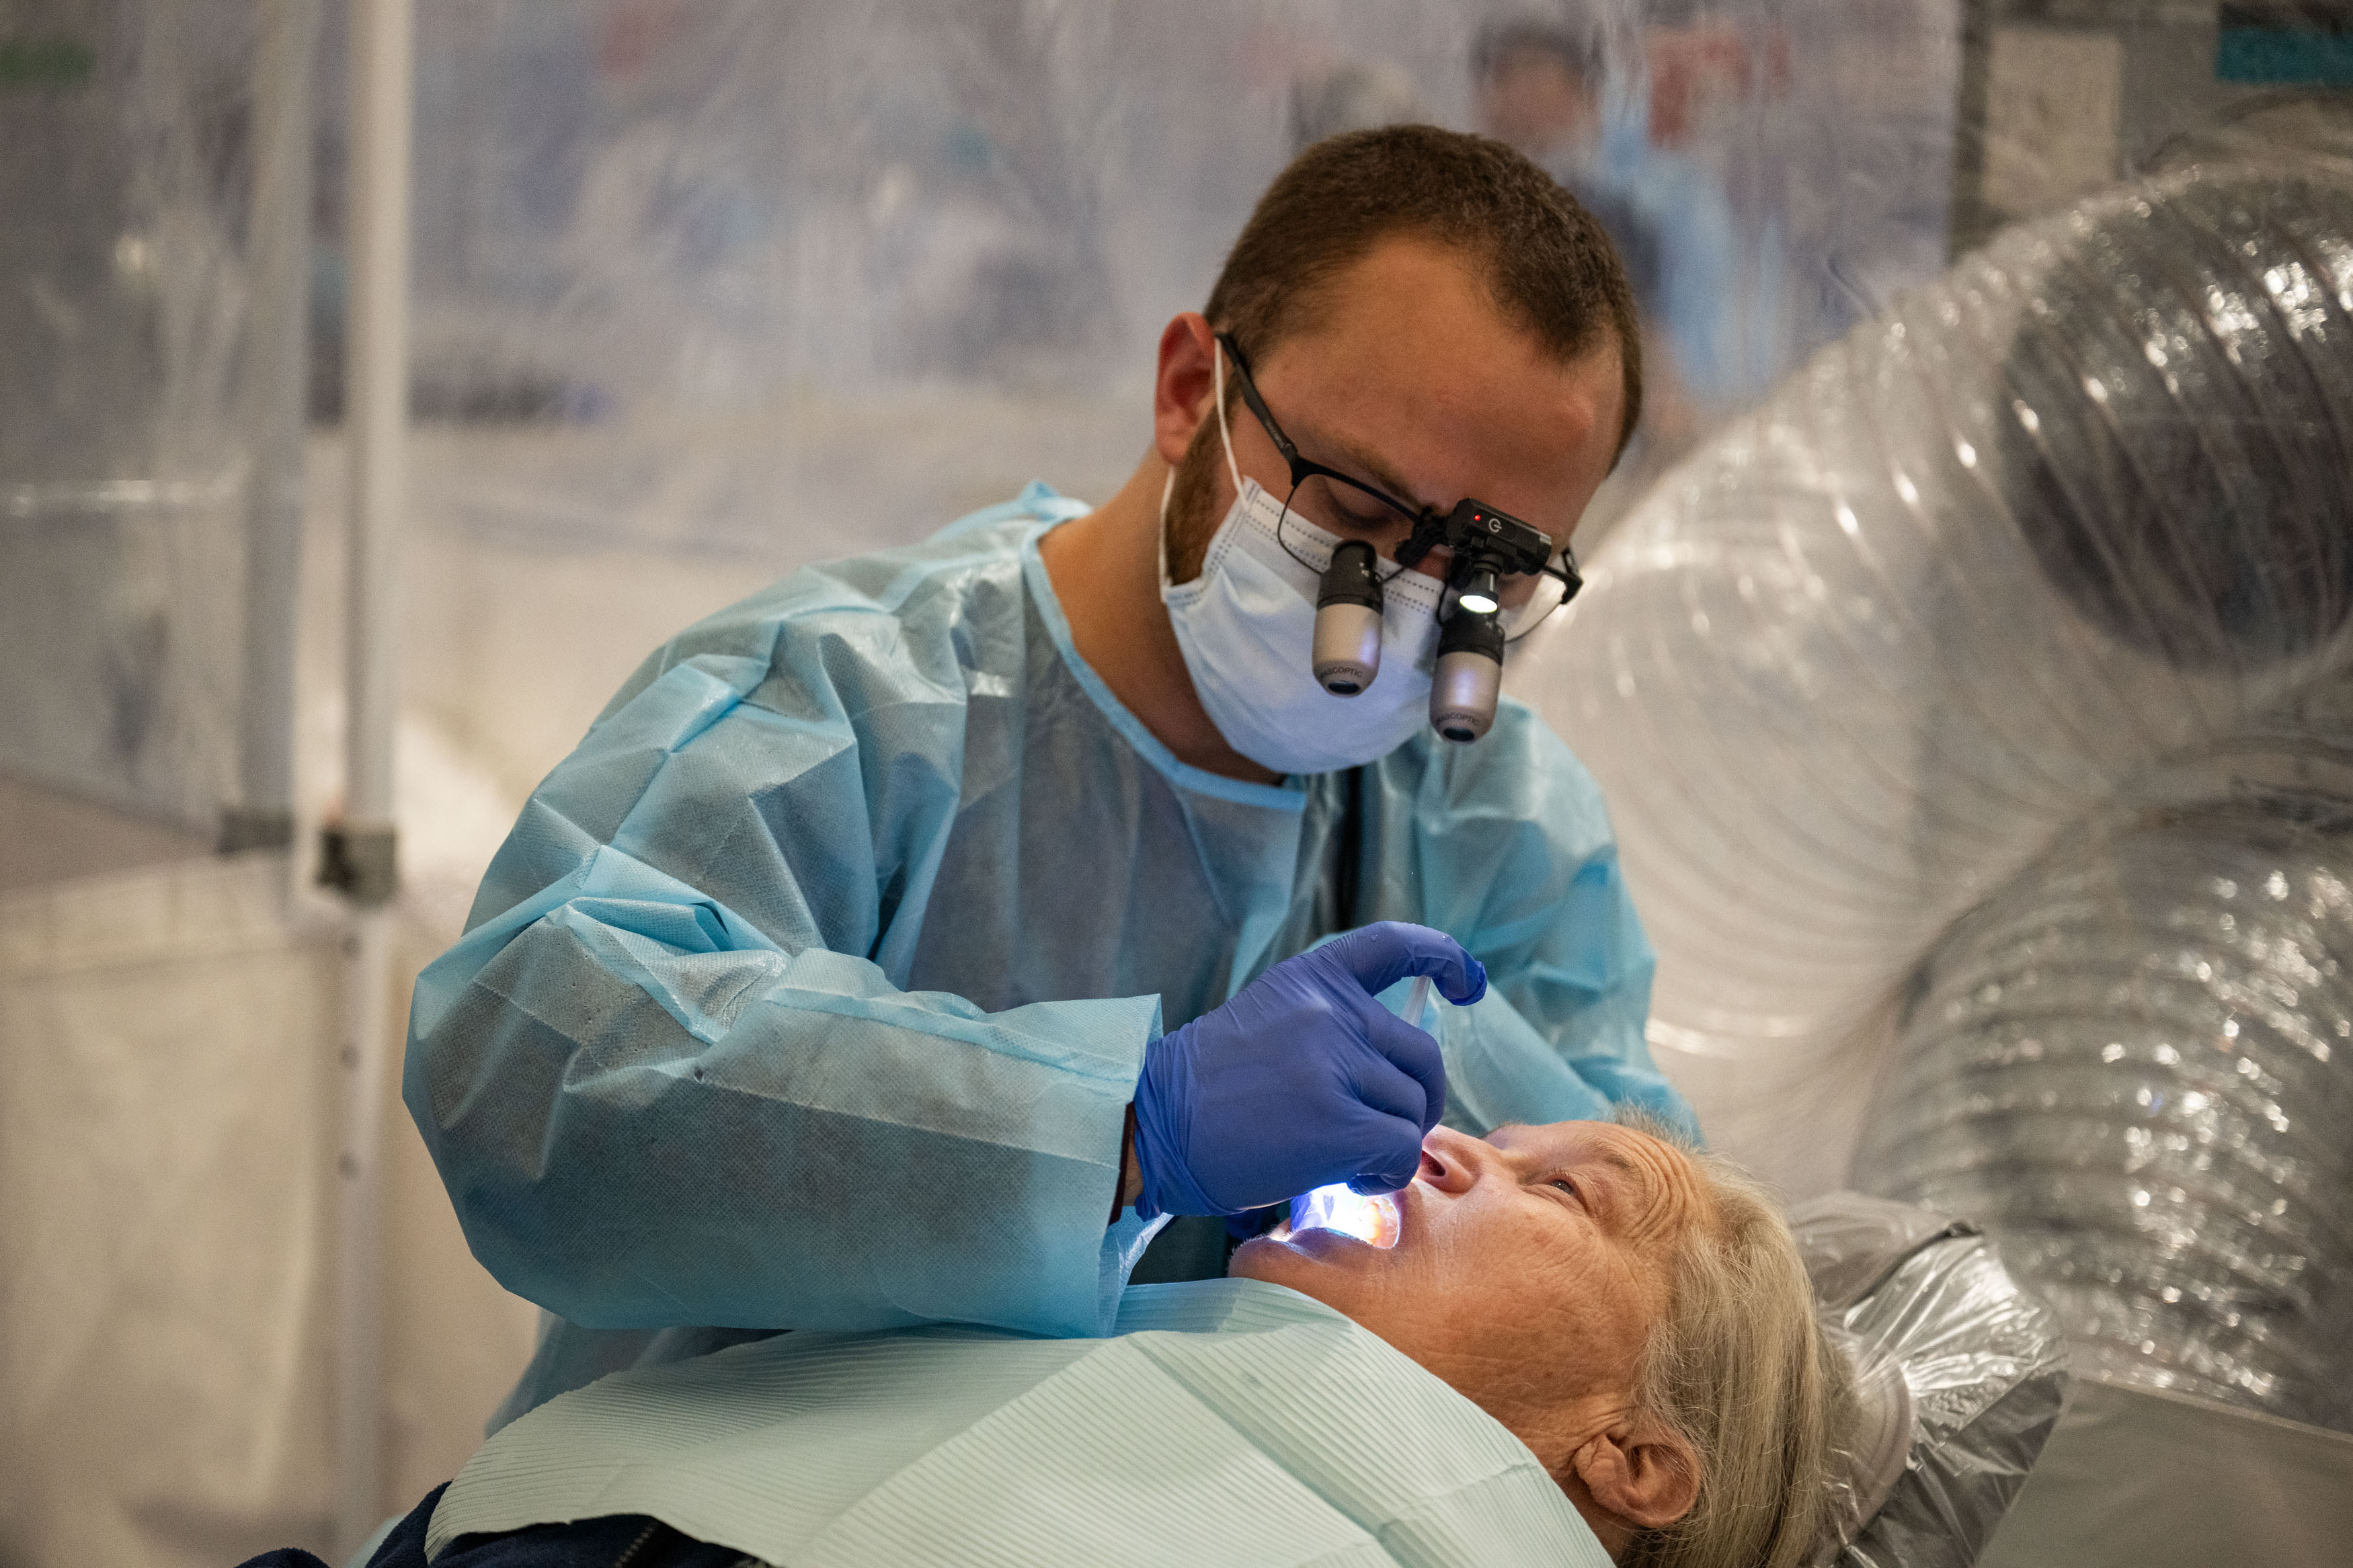
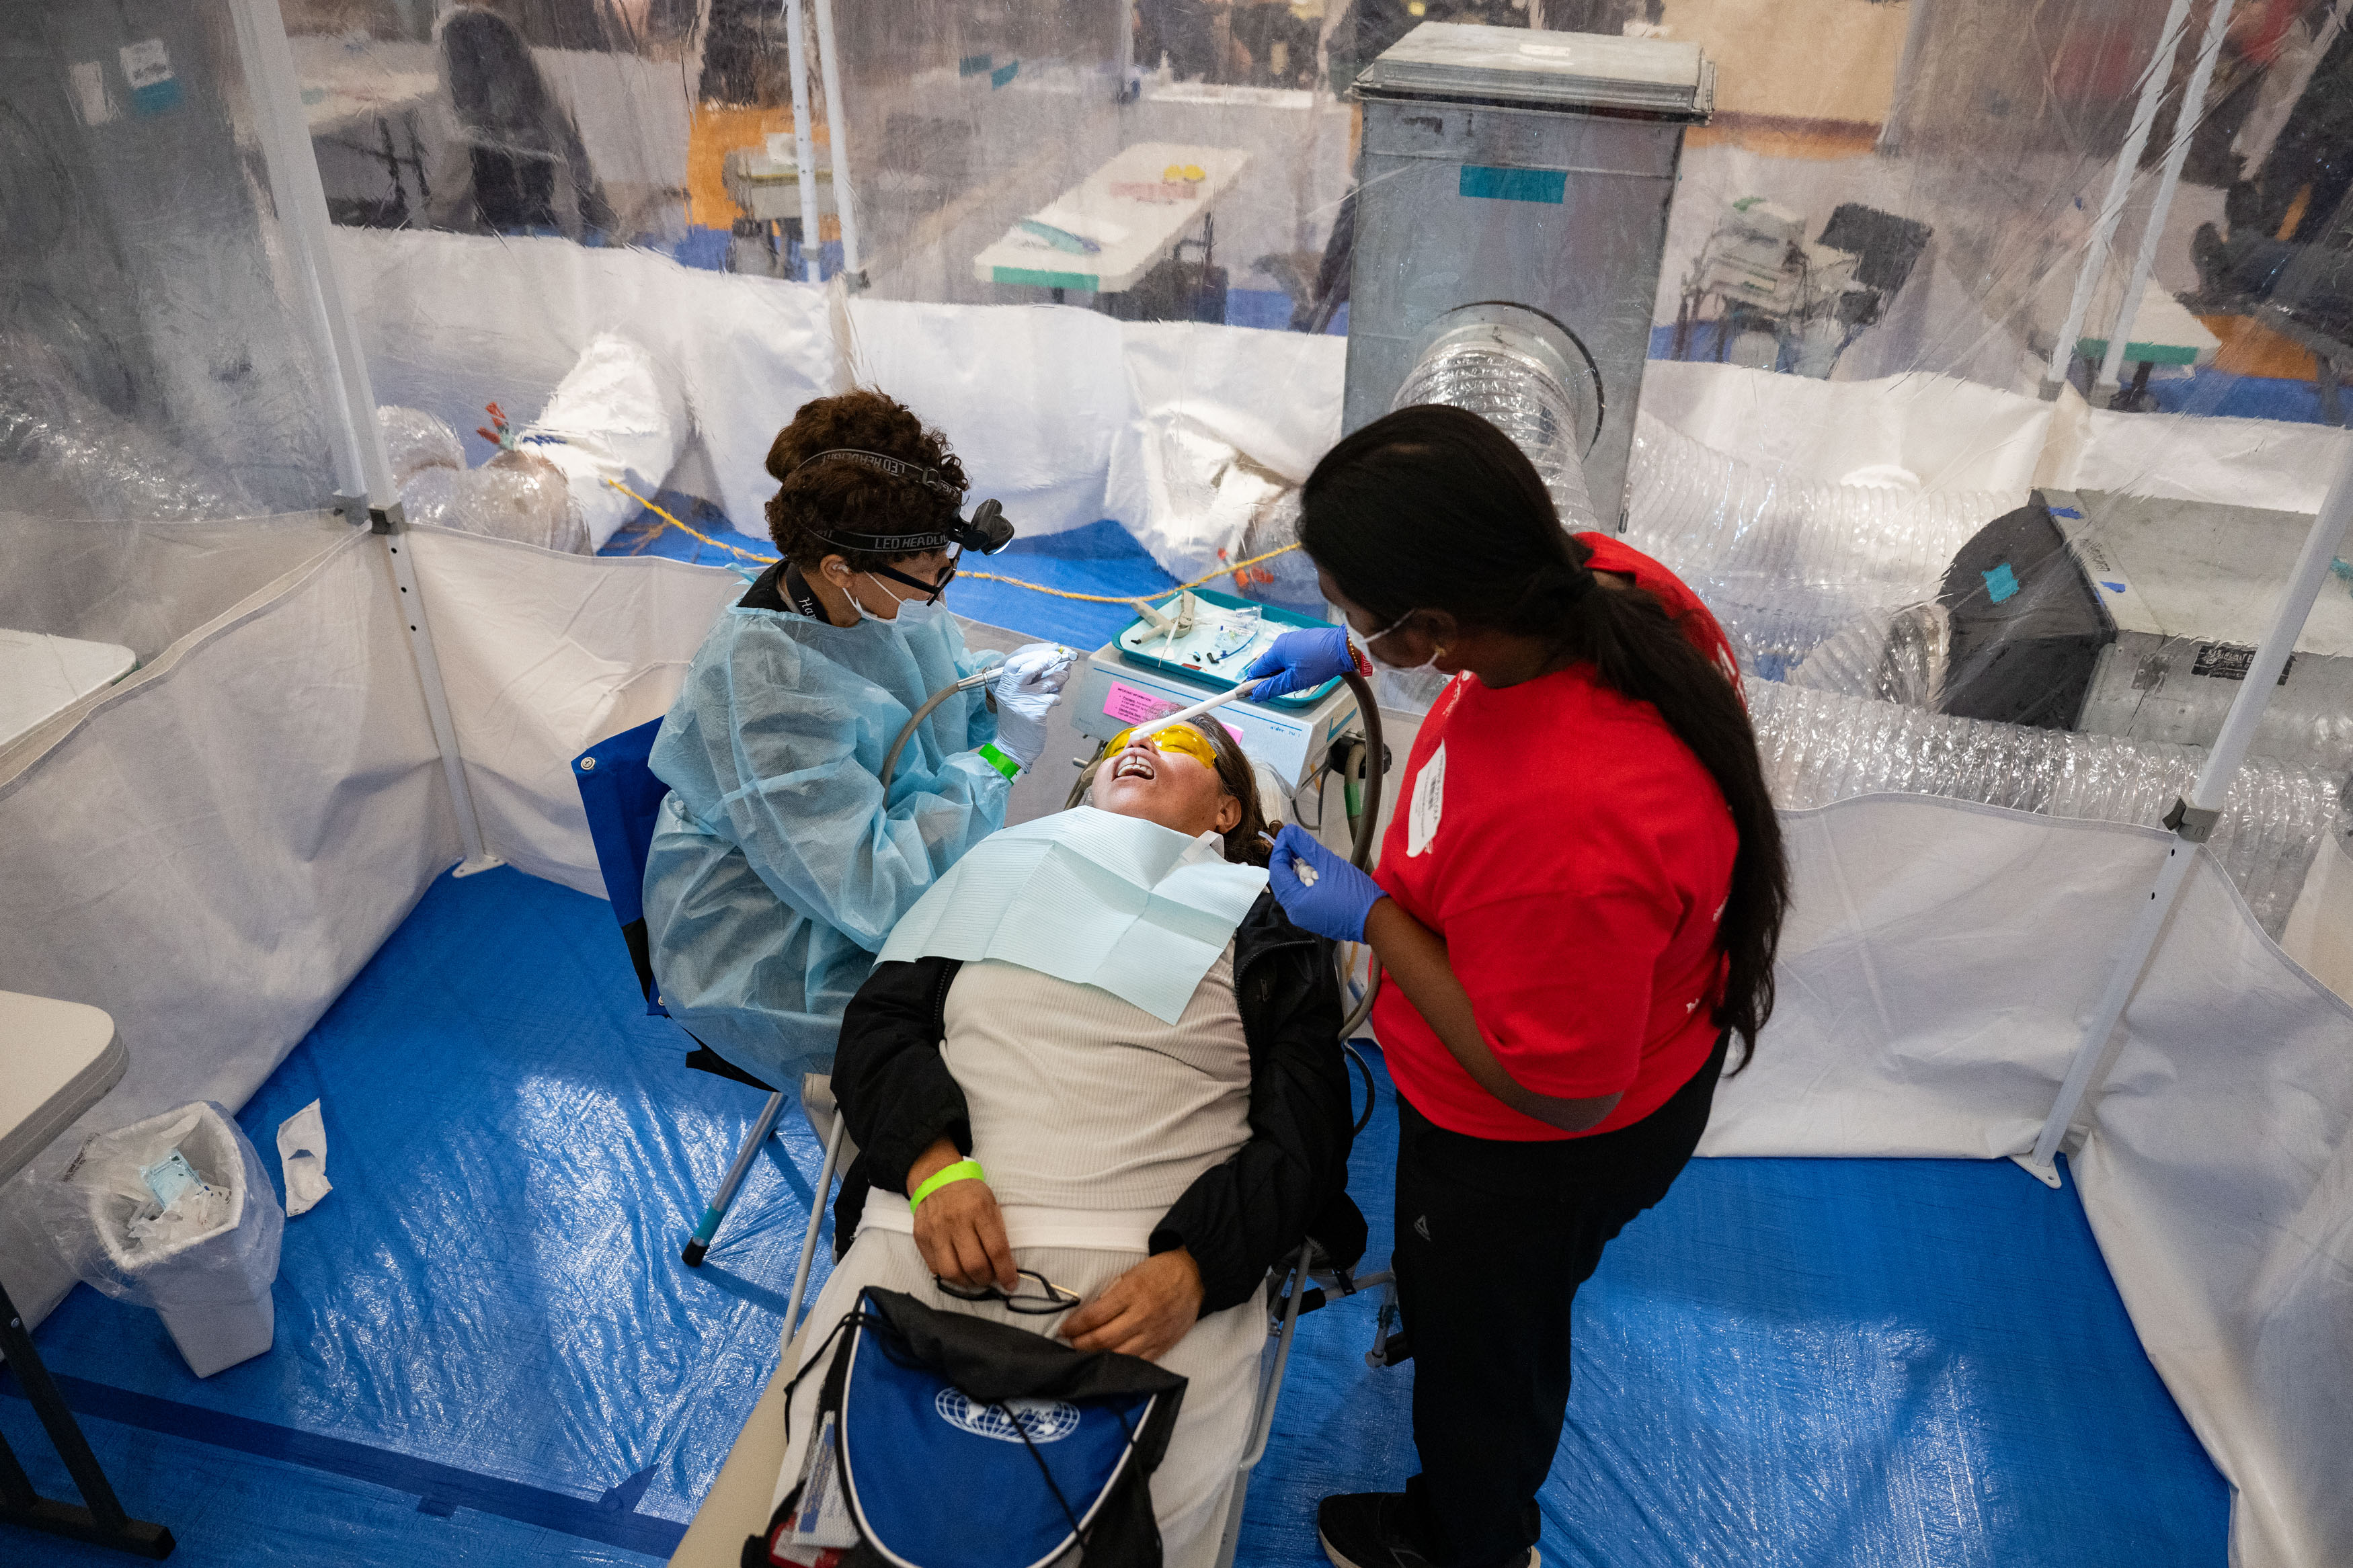
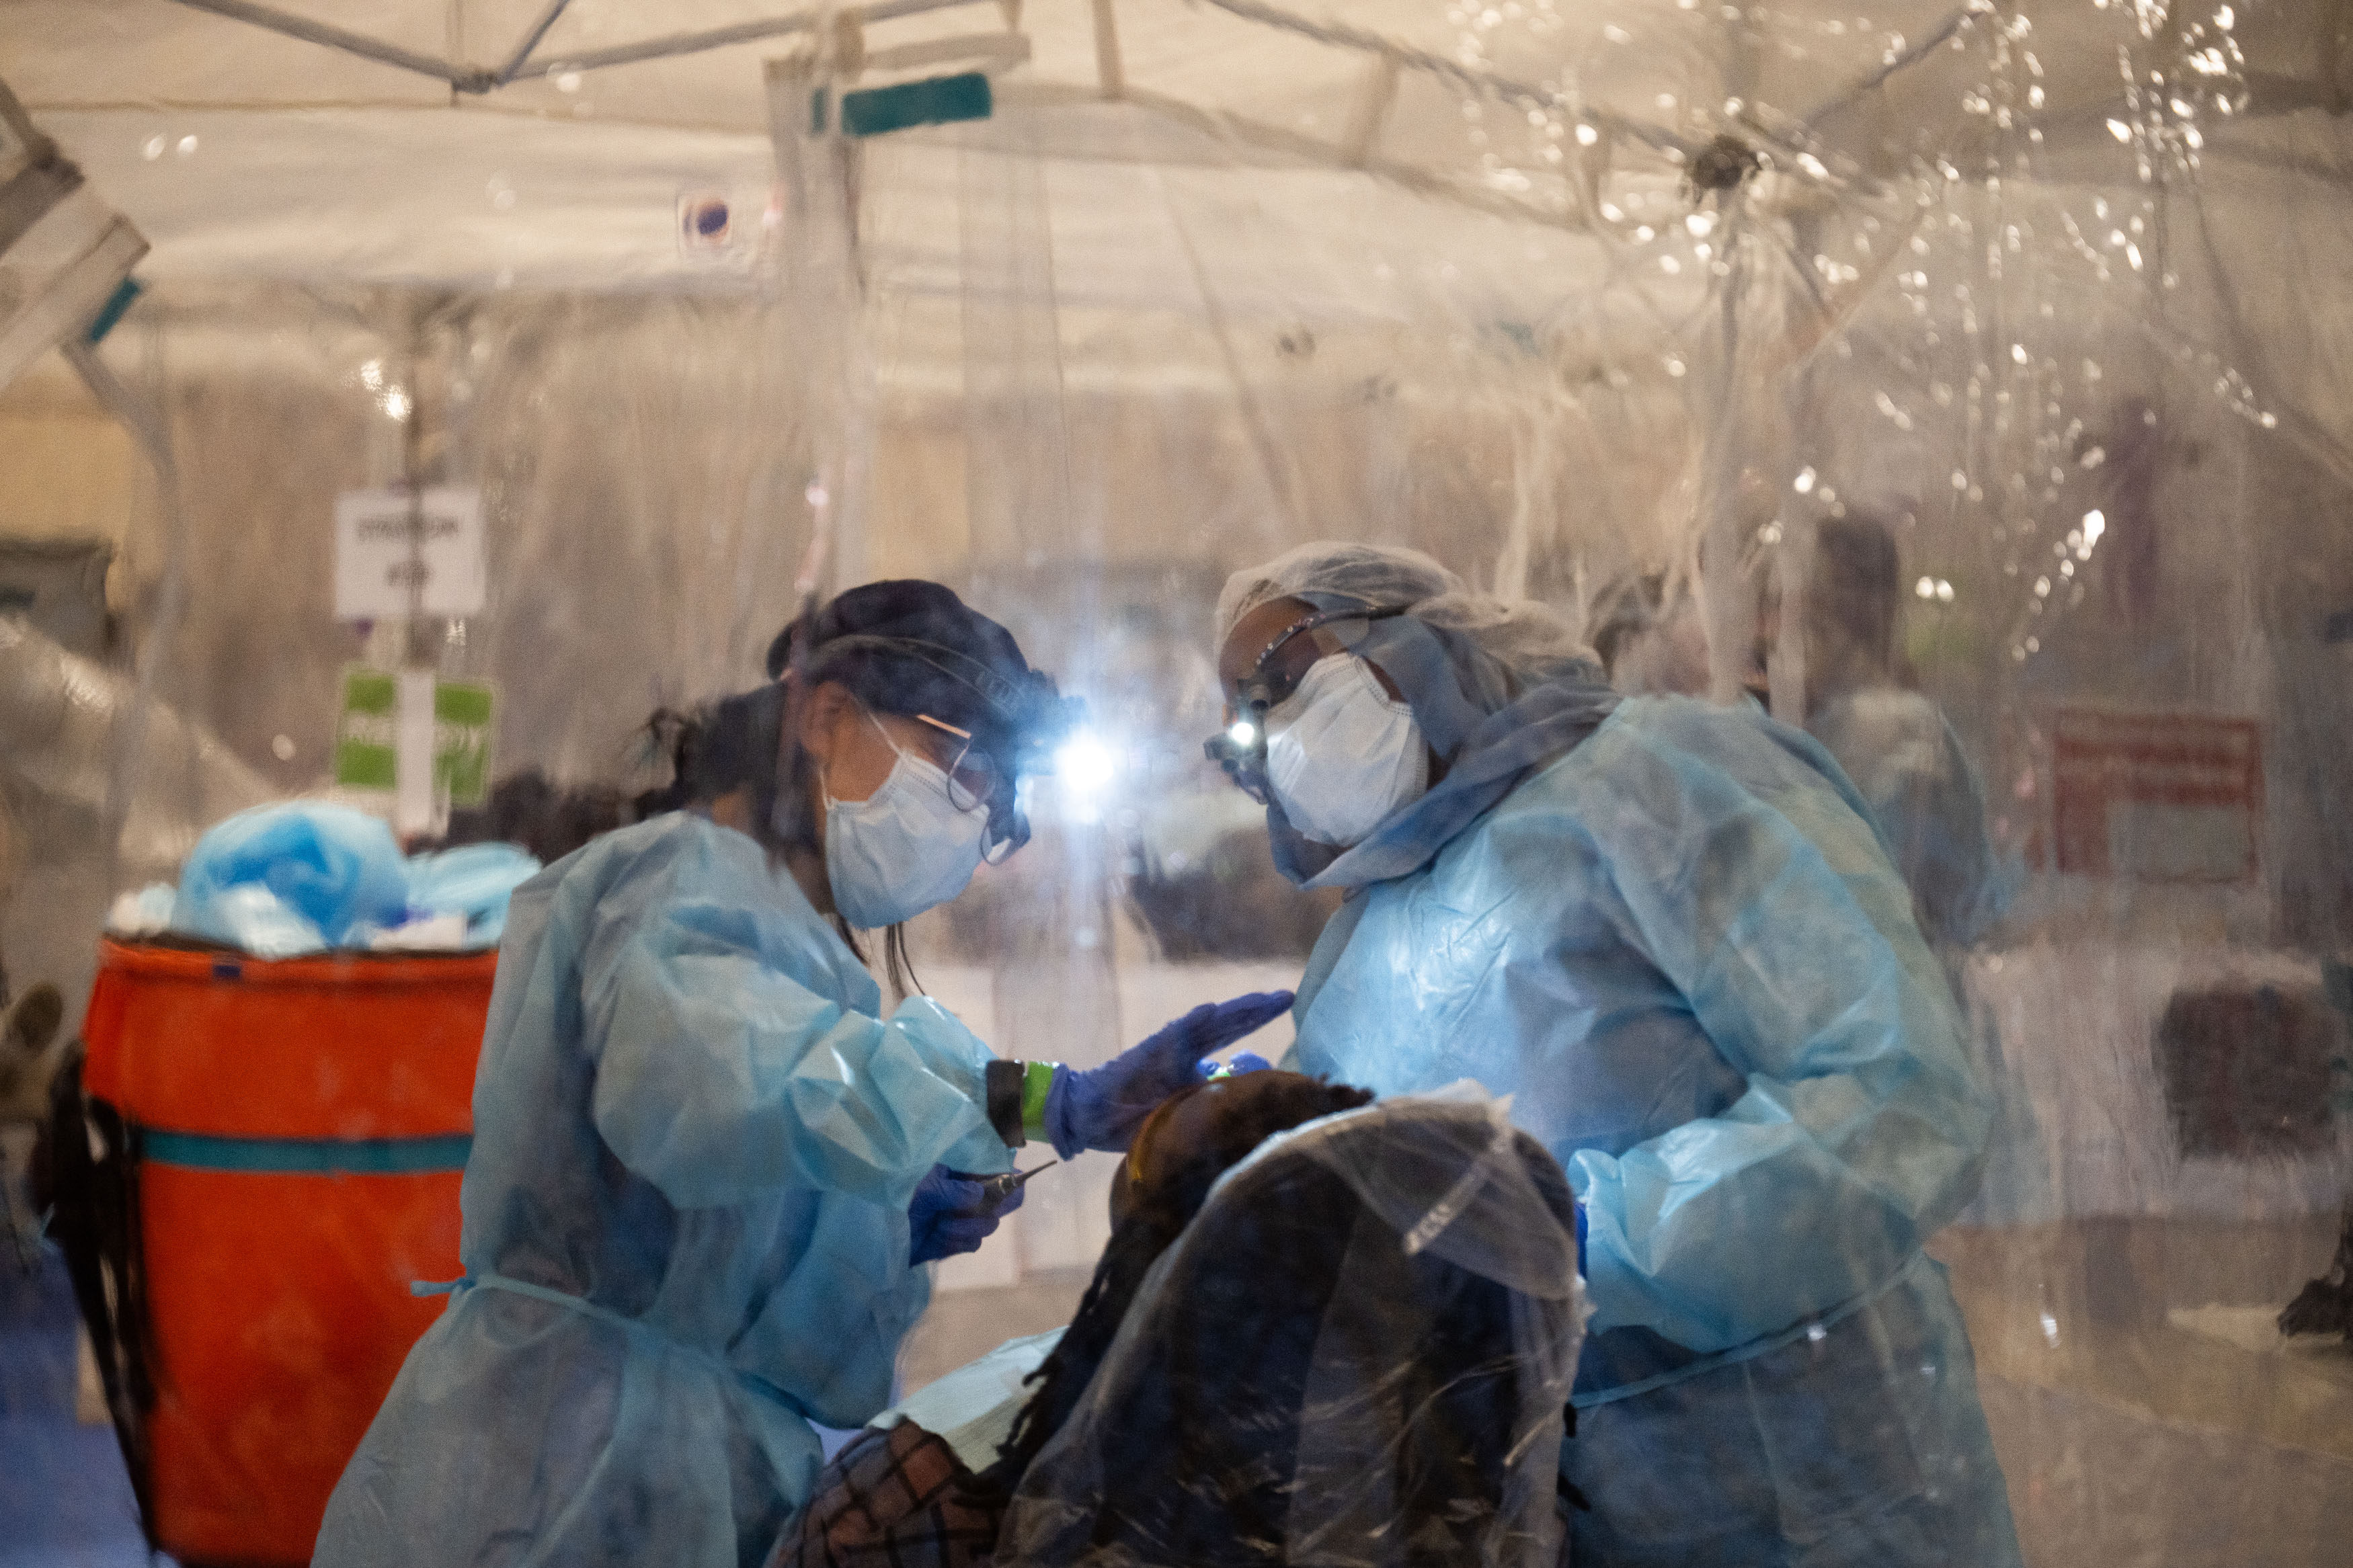
Around 11 a.m., Walton was in one of the 30 dental treatment tents set up in the large gymnasium, having her filling replaced.
“You got here just in time,” John Renzi, a dentist volunteering at the clinic, told her just before he began drilling. “Any longer and this tooth would have been a goner.”
Dentist John Renzi replaces a cracked filling for Alma Walton. (Eric Harkleroad/KFF Health News)
The clinic was organized by Remote Area Medical, a Tennessee-based nonprofit that says it has provided free healthcare to more than a million patients over its 40-year history. The clinics initially targeted rural areas, such as in Appalachia, traditionally home to some of the poorest and least insured communities in the country.
In recent years, the organization has branched out into urban and suburban areas — such as around the nation’s capital, Baltimore, and Philadelphia — where having insurance is more common. The clinics rely on doctors and dentists donating their time.
At the Takoma Park event, more than 300 dental, medical, and vision professionals volunteered along with members of the U.S. Public Health Service.
According to a survey by Remote Area Medical, nearly 40% of patients here said they had not seen a dental provider — other than one provided at a RAM clinic — in at least two years.
And nearly two-thirds said they did not have a usual place for seeking care other than a hospital emergency room.
Over 700 people volunteered to help at the free clinic. (Eric Harkleroad/KFF Health News)
According to a survey by Remote Area Medical, nearly 40% of clinic patients said they had not seen a dental provider — other than one provided at a RAM clinic — in at least two years. (Eric Harkleroad/KFF Health News)
Dana Bensinger, a nurse specialist working at the medical care clinic, said many patients had high blood pressure or diabetes. They were given prescriptions for a 90-day supply of pills and told to connect with community health centers or free clinics where they can get free or low-cost primary care.
“We have seen a lot of folks who lose insurance or are not able to keep it, and so they can’t get their prescriptions renewed,” he said.
Many patients at the clinic showed up to get a tooth extraction — and with it, relief from dental pain.
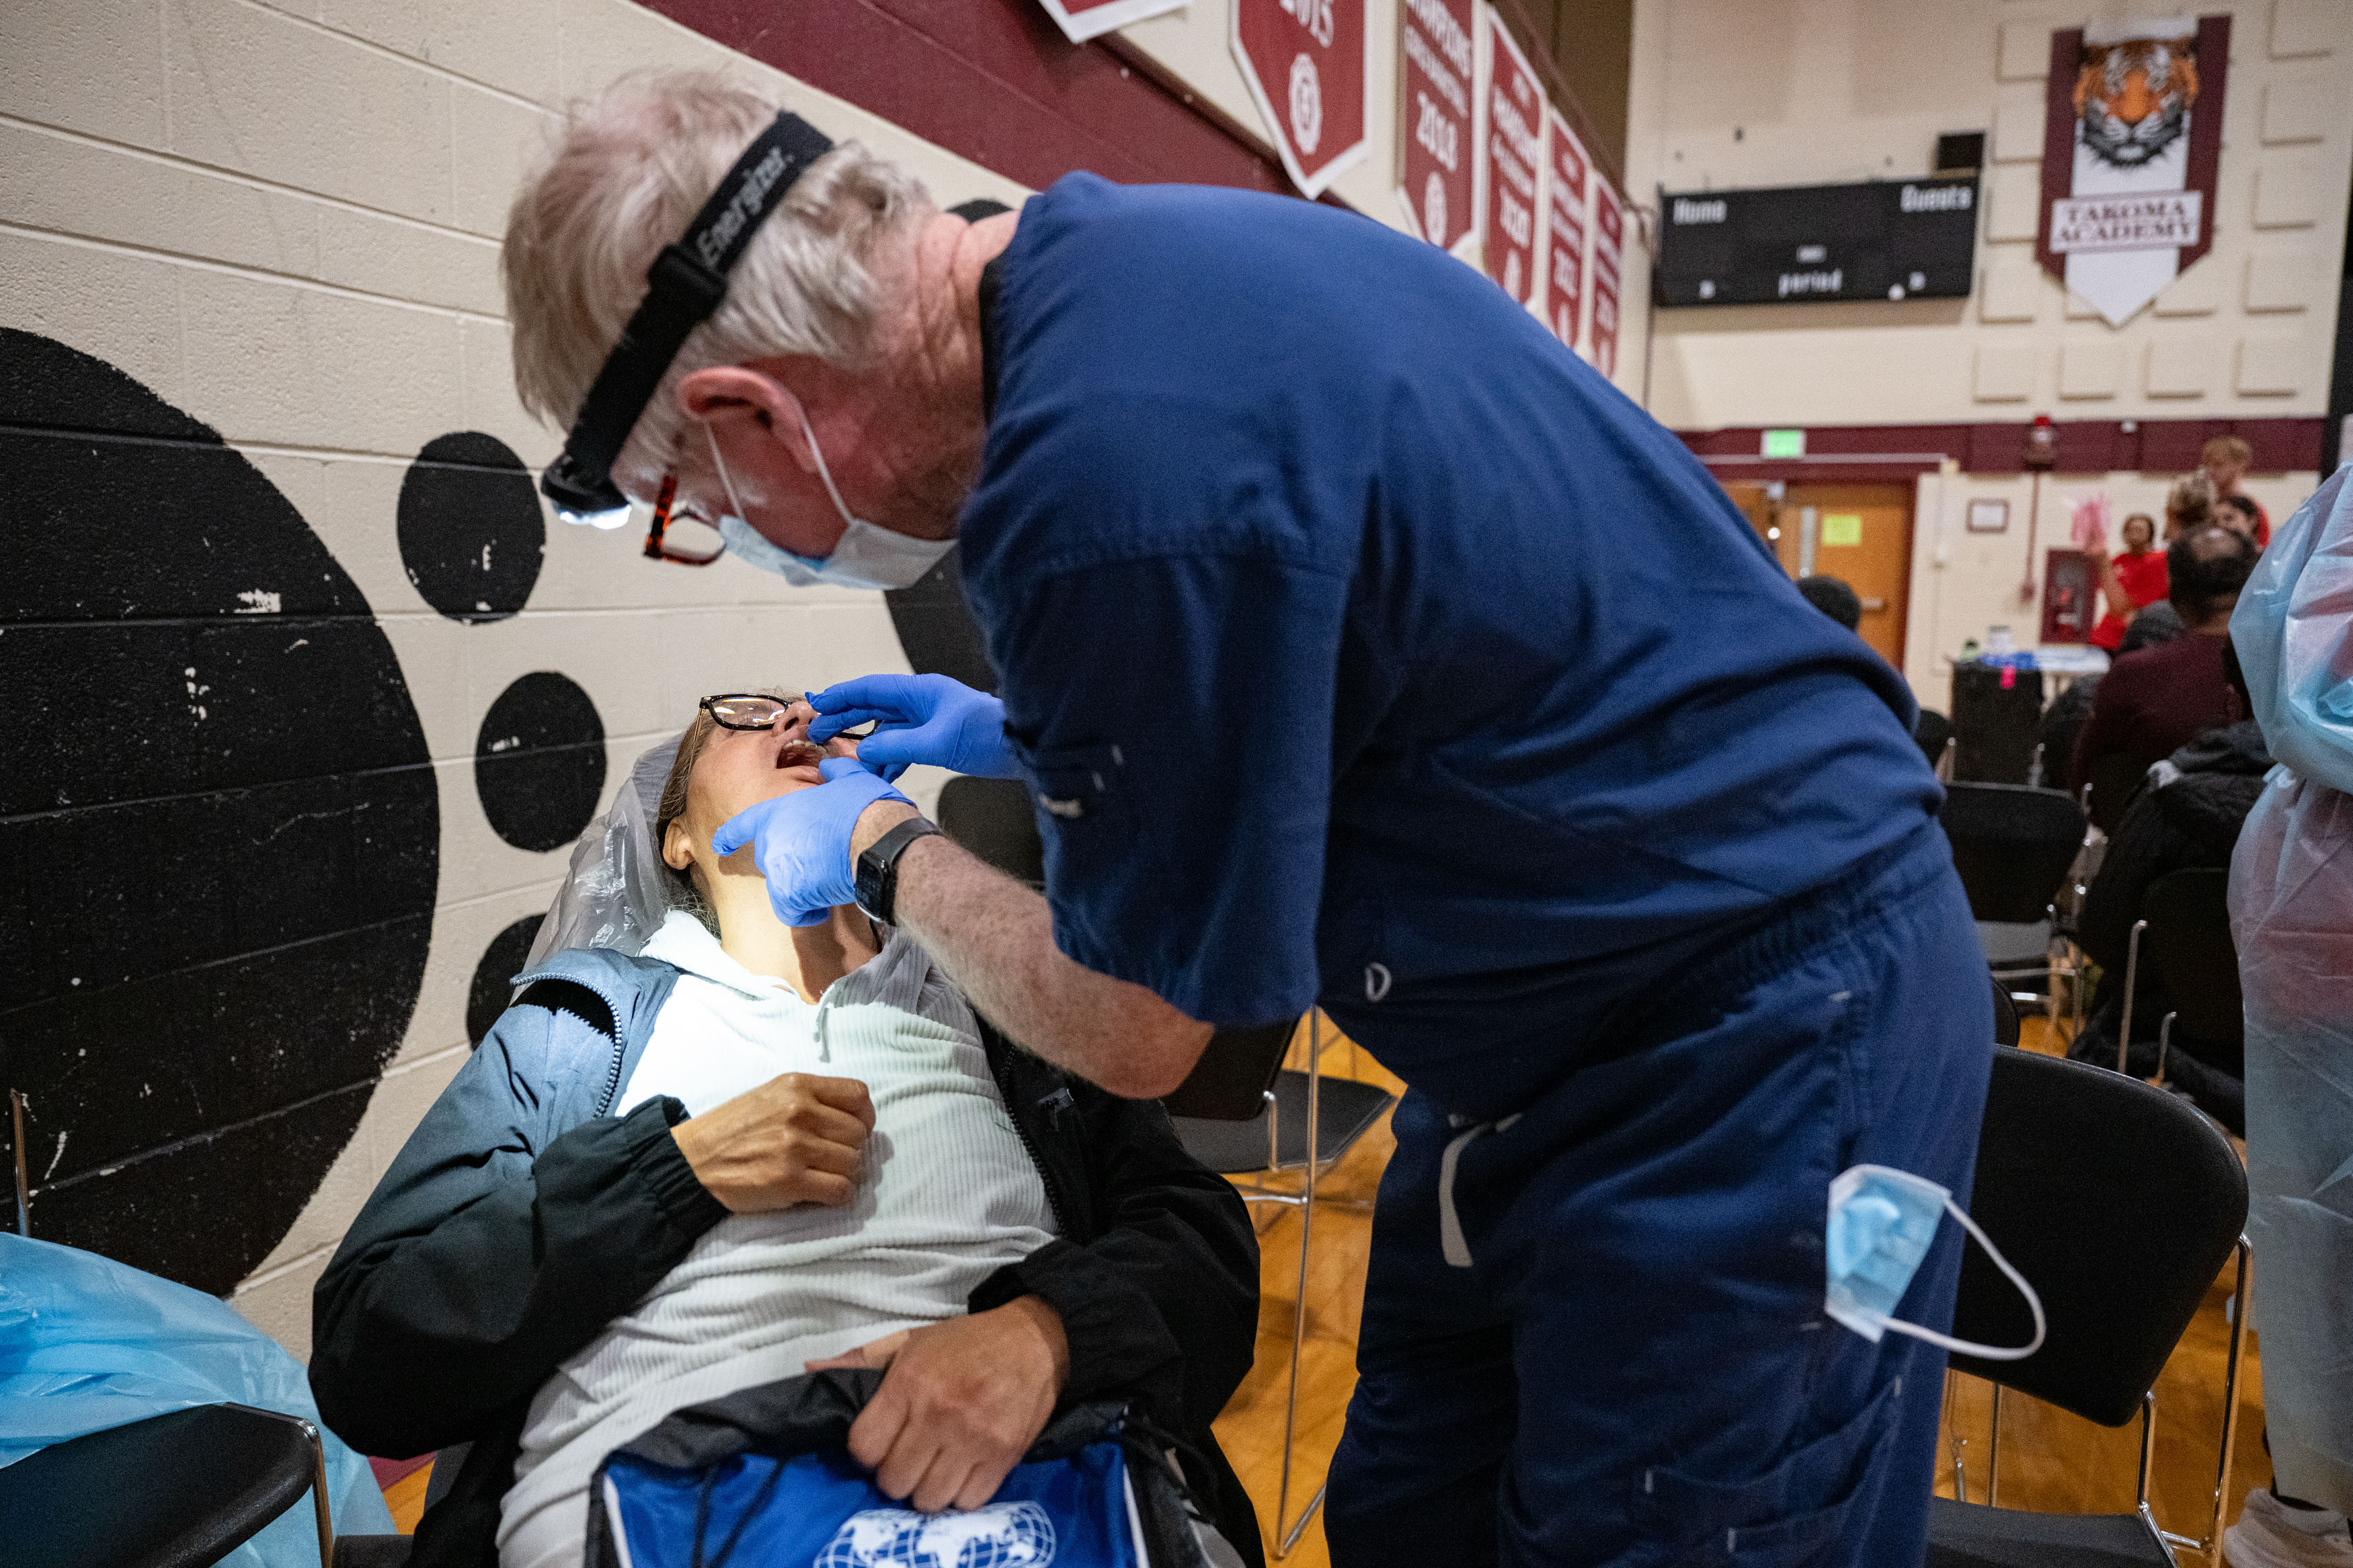
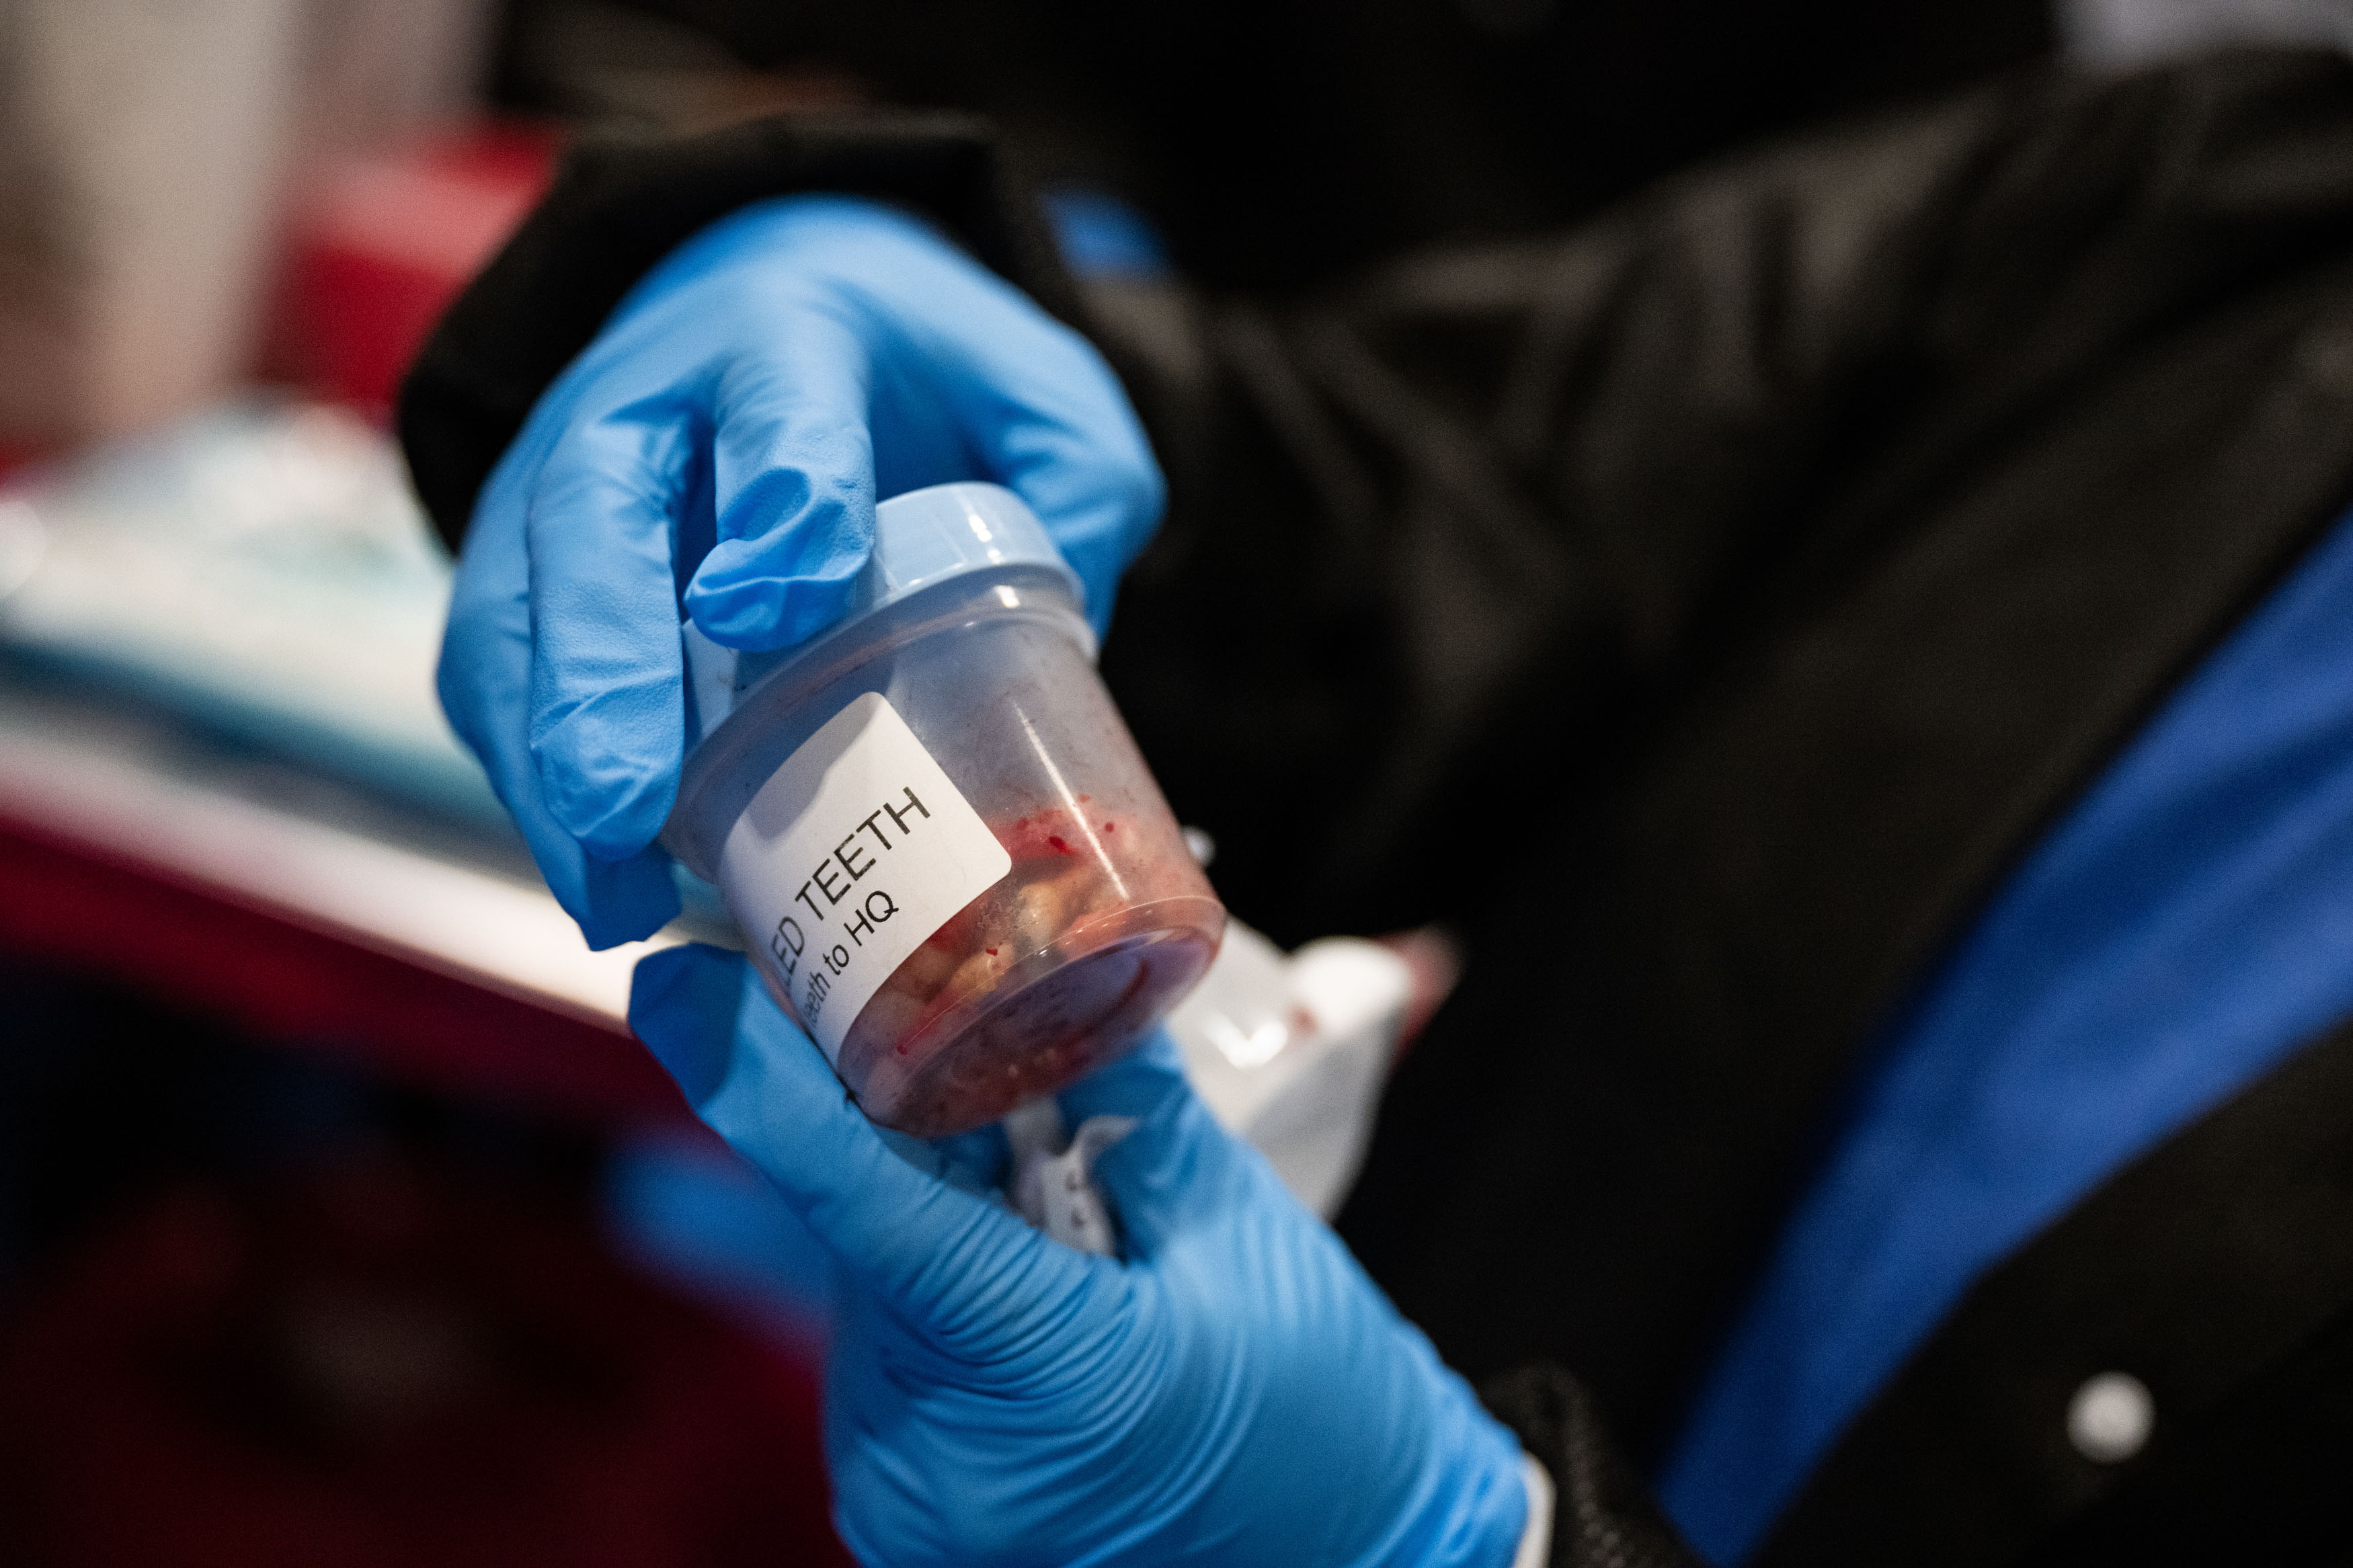
“We call it point-and-pull dentistry,” said Tom Ritter, a retired dentist who was triaging dental patients. “You point to the tooth you want out, and we take it out.”
Tom Ritter, a retired dentist, triaged dental patients at the free clinic. He examined Josefina Guel’s teeth, and she later received a filling. (Eric Harkleroad/KFF Health News)
A clinic volunteer shows a jar of patients’ extracted teeth. “We call it point-and-pull dentistry,” Ritter says. “You point to the tooth you want out, and we take it out.” (Eric Harkleroad/KFF Health News)
Dentist Marsha Plater fills a cavity for Josefina Guel with help from dental assistant Anusha Patlola. (Eric Harkleroad/KFF Health News)
The dilemma, he said, is patients often need multiple teeth extracted and the volunteer dentists have only limited time for each patient. “We have to spread the love around because we have a busy schedule.”
Michel Boudreaux, an associate professor at the University of Maryland Department of Health Policy and Management, said the RAM clinic, about 5 miles from his campus, highlighted the growing difficulty people with and without health insurance face.
“Even in this suburban county there are a lot of uninsured people struggling with affordability and insured people struggling with high deductibles and copays,” he said.
Boudreaux called it “disheartening” that people felt they had to sleep in their cars overnight for care.
Having a government job with benefits was once seen as way of immunizing one’s family from rising health costs.
Cheromie Johnson, who works for the District of Columbia, said that recent dental work left her with a $12,000 bill.
She came to the clinic with her 6-year-old son, Cairo, to get eye exams. She was hoping they would each get a new pair of eyeglasses.
“This is very important, especially for him in school, and I drive, so we both need to see clearly,” Johnson said. She estimated the free vision care would save them more than $1,000.
Cheromie Johnson’s 6-year-old son, Cairo, receives an eye exam at the clinic. (Eric Harkleroad/KFF Health News)
Ryan Shaw, a physician assistant student, checks Cairo’s eye pressure. (Eric Harkleroad/KFF Health News)
An assortment of frames provided free to vision patients at the clinic. The clinic made 152 pairs of eyeglasses for 99 patients. Some received reading and distance glasses. (Eric Harkleroad/KFF Health News)
When asked what this busy free clinic said about the state of U.S. healthcare, she said: “It’s poor, and it needs to be revamped. But we all know that.”
John Osborn, dental director for RAM, was taking a break on a balcony that overlooked the gymnasium, now peppered with treatment tents and mobile equipment that had transformed the space into something from the TV show M*A*S*H from decades ago. He was not surprised to see people showing up on a Saturday morning for care. Over the past 35 years, he’s seen similar scenes at RAM’s clinics across the country.
He only wished that some members of Congress would have come by to bear witness.
“It would have been nice for them to see what people have to do to get healthcare,” he said.
A patient has dental work done at the clinic. (Eric Harkleroad/KFF Health News)
KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.
Deadly outbreaks like the Ebola epidemic raging in the Democratic Republic of Congo show the urgent need to complete an international pandemic treaty, the World Health Organization chief said Monday. Pointing to several recent deadly disease outbreaks, he stressed that completing a pandemic treaty was "about protecting people".
from Top Health News | Latest Healthcare Sector & Healthcare Industry news, Information and Updates: ET HealthWorld : ETHealthworld.com https://ift.tt/ywPZMef
Healthcare recorded 28 PE/VC deals in Q3 2026, up from 19 in the previous quarter, with September alone accounting for 11 deals.
from Top Health News | Latest Healthcare Sector & Healthcare Industry news, Information and Updates: ET HealthWorld : ETHealthworld.com https://ift.tt/2CjKrnB
When U.S. Rep. David Valadao defended voting for a bill aimed at reducing Medicare spending by billions, the Republican noted his role in securing a key provision that will require some adult beneficiaries to work — a mandate he called “not an unreasonable ask.”
But the voters in his California Central Valley district, home to one of the most competitive House races in the nation, might get a pass from the Medicaid work rules in the One Big Beautiful Bill Act, which President Donald Trump signed into law last summer.
Starting in January, the law requires many nondisabled adults enrolled in Medicaid in 43 states and Washington, D.C., to work, volunteer, or go to school for at least 80 hours a month. But those who live in counties where a high number of people are out of work could get relief — one of several carve-outs in the law.
“Based on current numbers, every county in CA-22 would qualify for this exemption,” Valadao’s website says, referring to his district. “This waiver is important because it takes real-life situations into account, and if someone is trying to work but opportunities are limited, they won’t be required to.”
The congressman, who has said enrollees in Medicaid — the federal-state program covering the poor and disabled — should “put in a fair day’s work” if they can, declined an interview request. Valadao campaign spokesperson Paige Ash also declined to comment.
Valadao (right) introduces U.S. House Speaker Mike Johnson on Sept. 30 at a campaign event in Bakersfield, California. (Jackie Fortiér/KFF Health News)
Valadao is among at least 21 Republican lawmakers running for reelection who voted for the 2025 GOP bill and represent counties that could qualify for a hardship exception, according to a KFF Health News analysis.
Roughly 6 in 10 residents in Valadao’s district are enrolled in Medi-Cal, the state’s Medicaid program. Researchers have estimated 60,000 more residents of his district could be without coverage by 2034 as a result of the One Big Beautiful Bill and the expiration last year of enhanced premium tax credits for Affordable Care Act insurance plans.
“It feels akin to an arsonist trying to take credit for helping put out a fire that they themselves ignited when all of this was avoidable pain from the outset,” said Miranda Yaver, an assistant professor of health policy and management at the University of Pittsburgh.
Valadao faces Democrat Randy Villegas in a district that was redrawn last year to lean more blue, and the two sides had each booked more than $16 million in advertising through Election Day, according to data compiled by AdImpact. Villegas and other Democratic challengers nationwide have made Republicans’ Medicaid vote a centerpiece of their campaigns, saying most enrollees already work, are disabled, or are caregiving.
The law allows states to apply for a short-term hardship exception for enrollees who live in counties where unemployment is at least 8%, or at least 1.5 times the national rate, whichever is lower. But it’s unclear how the Trump administration intends to implement that relief.
Some states have yet to submit their applications. Five Democratic-led states have asked the federal government to delay the work requirements, citing insufficient time to comply before the end of the year.
The press office for the federal Centers for Medicare & Medicaid Services, which is implementing the new law, told KFF Health News in an unsigned email that states may submit unemployment data from a “reliable” source, including figures from their own labor departments. But the agency hasn’t said exactly what time frame of unemployment data states should provide.
A small group of protesters outside Valadao’s Bakersfield office on Sept. 30. They chanted that healthcare costs are too high, blaming Republican elected officials including Valadao. (Jackie Fortiér/KFF Health News)
Unemployment data can be reported in a variety of ways. It can be from the most recent month, or a 3-, 6-, or 12-month average. That data will determine how many counties — and how many people — might qualify.
Using July 2026 unemployment rates, which are not adjusted for seasonal swings, 95 U.S. counties would qualify for the exception, according to an analysis by KFF, a health information nonprofit that includes KFF Health News. Using the 12-month average, the number of qualifying counties jumps to 120.
“Which data is used matters,” said Jennifer Tolbert, deputy director of KFF’s Program on Medicaid and the Uninsured. “I think there’s a lot still unknown.”
Sixty-four counties have high unemployment rates that will most likely qualify them no matter what data is used. The vast majority of the counties have a Republican representative. CMS declined to say how long exceptions would last or which states have applied. Indiana, Iowa, and Missouri do not plan to seek the hardship exception, according to KFF’s Medicaid work requirements tracker.
Some states are waiting for answers. California is among those that have asked to push back the start date. In September, the state asked CMS for permission to use state unemployment data that it says is timelier than federal data. State officials are waiting for a response, as well as for details about how long exemptions could be granted, said Griselda Melgoza, a spokesperson for the California Department of Health Care Services.
While blue states like California are seeking exceptions to help minimize the fallout of the new Medicaid rules, Yaver said any exceptions to the work rules could serve Republicans politically in the future.
“I think that exemptions and strategic burden reduction will ultimately undercut the accountability,” she said. “Because voters will just not really see the full reach of the law.”
KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.
With drugs belonging to the glucagon-like peptide-1 (GLP-1) receptor agonist class gaining attention for weight management, specialists have cautioned that women with PMOS need an individualised treatment plan based on their symptoms, weight, metabolic health and reproductive goals.
from Top Health News | Latest Healthcare Sector & Healthcare Industry news, Information and Updates: ET HealthWorld : ETHealthworld.com https://ift.tt/Gs57dON
With an investment of approximately Rs. 600 crore, the Centre will be India's first proton therapy facility to be established by a State Government. It will bring one of the world's most advanced forms of radiation-based cancer treatment closer to patients in the Northeast, while positioning Assam as a major hub for specialised cancer care.
from Top Health News | Latest Healthcare Sector & Healthcare Industry news, Information and Updates: ET HealthWorld : ETHealthworld.com https://ift.tt/Myl6kWD
Operational bed capacity at end of September stood at 5,518, up by 758 beds and 16 per cent YoY compared to Sep 2025. Bed occupancy for the quarter was at 77 per cent, with Occupied Bed Days (OBDs) up by 13 per cent YoY.
from Top Health News | Latest Healthcare Sector & Healthcare Industry news, Information and Updates: ET HealthWorld : ETHealthworld.com https://ift.tt/AIXRekj
What’s scarier than ghosts and goblins? How about measles, unaffordable dental care, and an insurance claim denied by artificial intelligence?
Nearly 80 healthcare-themed haikus crept into our inbox this Halloween season. Meet the winners of KFF Health News’ eighth annual Halloween haiku contest below.
Follow KFF Health News’ social media accounts (X, Instagram, and Facebook) for more of our favorites. Enjoy!
1st Place
(Illustration: Oona Zenda/KFF Health News; Haiku: DJ Zelle)
Which is scarier? Jack-o’-lanterns and ghouls, or Measles and lettuce?
— DJ Zelle
2nd Place
(Illustration: Oona Zenda/KFF Health News; John Fedyna)
Drac on a budget: His fangs are ineffective, Dental too costly.
While Halloween may be coming to an end, KFF Health News reporting continues year-round. Send us your haikus at any time for possible inclusion in our Morning Briefing: https://kffhealthnews.org/contact-haiku/.
2025 Halloween Haiku Contest Winners
2024 Halloween Haiku Contest Winners
(Illustration: Oona Zenda/KFF Health News; Haiku: Crystal Decker) (Illustration: Oona Zenda/KFF Health News; Haiku: Sasha Zitter) (Illustration: Oona Zenda/KFF Health News; Haiku: Siri Palreddy)
2023 Halloween Haiku Contest Winners
(Illustration: Oona Zenda/KFF Health News; Haiku: Madeline Steward) (Illustration: Oona Zenda/KFF Health News; Haiku: Tom Cook) (Illustration: Oona Zenda/KFF Health News; Haiku: Brynne McBride)
2022 Halloween Haiku Contest Winners
(Illustration: Oona Zenda/KFF Health News; Haiku: Paul Hughes-Cromwick) (Illustration: Oona Zenda/KFF Health News; Haiku: Micki Jackson) (Illustration: Oona Zenda/KFF Health News; Haiku: Michael L. Millenson)
KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.
When Ashley Porter began slurring her speech one October day four years ago, doctors suspected a stroke. A spinal tap, an MRI, dozens of blood draws, another MRI, and a night spent at the hospital were followed, finally, by an answer: Porter had multiple sclerosis.
Her shock turned to outrage, she said, when she received the roughly $180,000 hospital bill, even though insurance covered most of it.
Porter and her husband have insurance through two separate employer plans yet have spent at least $75,000 a year — roughly a quarter of their gross income — on medical expenses since her diagnosis.
“It is terrifying,” said Porter, who works in transportation sales in the San Francisco Bay Area. “I can’t imagine having this disease and not making the kind of income that we make.”
The average premium for a California family with employer-sponsored coverage has hit nearly $28,400 a year, up 24% since 2022, much more than workers’ wages. Amid skyrocketing healthcare costs, the gubernatorial candidates’ proposals remain short on specifics about funding or implementation to address this top priority for voters in the nation’s largest healthcare market.
“People are hungry for pretty aggressive action on healthcare spending,” said Kristof Stremikis, director of market analysis and insight at the California Health Care Foundation, a nonprofit philanthropic organization specializing in healthcare research and education.
“Regardless of who our new governor is and who our new state policymakers are in the next year, they have a mandate,” he said.
Nearly two-thirds of Californians worry about receiving an unexpected medical bill, surpassing financial concerns such as the cost of rent or food, according to a 2025 CHCF-NORC survey. Six in 10 said they or a family member had skipped care because of cost.
He has also said that Congress should restore an estimated $900 billion in federal Medicaid cuts and reinstate enhanced Affordable Care Act tax credits that President Donald Trump and the Republican-controlled Congress allowed to expire, causing insurance premium payments to increase for millions of Americans. Both are national Democratic priorities outside a governor’s purview.
Former Fox News host Steve Hilton, Becerra’s Republican opponent, has said he’d build on existing state laws governing price transparency and prescription drug middlemen known as pharmacy benefit managers to lower costs. And he wants to partially replace Medi-Cal, the state Medicaid program, with personal healthcare accounts of up to $10,000 a year — a concept unlikely to gain traction in a statehouse controlled by Democrats.
Both candidates declined multiple interview requests to discuss their health policies.
Xavier Becerra, the Democratic candidate for California governor, mingles with
supporters at a rally in Santa Rosa on Oct. 8. (Christine Mai-Duc/KFF Health News)
Steve Hilton, Republican candidate for California governor, speaks to the media at a campaign event on June 11. (Eric Thayer/Los Angeles Times via Getty Images)
Healthcare Costs and Consolidation
From 1970 to 2025, U.S. health expenditures ballooned from $75 billion to a projected $5.7 trillion, rising nearly 40% from 2020. By 2032, the Centers for Medicare & Medicaid Services predicts, health spending will account for more than a fifth of the U.S. economy.
Payments to hospitals, doctors, and clinics account for much of the inflation, along with rising prescription drug prices. Research shows that escalating mergers among physician practices, hospital groups, and insurers further stifled competition and raised prices.
In the 2018 lawsuit Becerra filed against Sutter Health, he accused the health system of using its market dominance to drive up hospital prices in Northern California, where procedures cost as much as 30% more than in other parts of the state.
The Sacramento-based not-for-profit system, which admitted no wrongdoing, paid an unprecedented $575 million fine and agreed to stop certain business practices, including imposing “all-or-nothing” terms on insurers that forced them to contract with the system’s entire network of clinics and hospitals.
“It was the biggest victory in antitrust and hospitals ever,” said Richard Scheffler, director of the Nicholas C. Petris Center on Health Care Markets and Consumer Welfare at the University of California-Berkeley. A report by the center, which conducts economic research on health policy topics, formed the basis of Becerra’s suit.
“But things change,” Scheffler said.
While the settlement likely discouraged similar practices by other hospital chains, he said, any relief has since been eclipsed by rapid consolidation in the healthcare industry.
At a press event in October, Becerra said he would work with the next state attorney general to “continue to look at the types of practices in healthcare that drive up costs.”
Hilton has said that he wants to increase competition by producing more generic drugs through California’s CalRx initiative, which aims to cut drug prices. He has said he wants to allow consumers to pick cheaper, pared-down insurance plans and force healthcare providers to make their prices more transparent.
Hospitals Under the Scope
Health economists say rising healthcare costs eat up money that employers might otherwise use for raises or new hires, depressing wages. That can be a double whammy for workers already struggling to meet basic needs and, consumer advocates warn, could increase medical debt, which 40% of California adults already report carrying.
Kia Frazier-Hill and her husband didn’t expect to be among them. She knew it would be expensive when he landed in the emergency room and was hospitalized at an out-of-network facility.
The astronomical prices gave her sticker shock: $17,507 for a night in the intensive care unit; $427.89 for a test for flu, covid, and RSV, or respiratory syncytial virus; $2.60 for a single tablet of generic, regular-strength Tylenol. Their bronze-tier plan from Covered California, the state’s ACA insurance marketplace, paid the vast majority, nearly $60,000, but the $7,500 balance has been in collections for months.
“We’re drowning,” Frazier-Hill said. “It just doesn’t make any sense what they’re charging.”
Researchers have found that hospital prices are even higher in uncompetitive markets.
California is trying to corral such runaway health costs through its Office of Health Care Affordability, which has directed most health systems, hospitals, insurers, and large healthcare provider groups to hold their spending growth to 3.5% this year.
Hospital and doctor groups, which have donated to Becerra’s campaign, say the cap is too low and will limit patient care, not improve efficiency.
“Hospitals have a mission to take care of people, save lives, and that costs money,” said Amber Ott, senior vice president of financial policy for the California Hospital Association, which is challenging the affordability board’s caps in court. “It’s hard to look at just one piece of the ecosystem and say that’s where the problem is.”
While hospitals are not the only drivers of high costs, they are the largest. According to the state, at least 40% of total health spending by commercial insurance plans went to hospitals in 2024, the latest data available.
People gather for an Aug. 13 town hall focused on high healthcare costs hosted by
Health Access California, a health consumer advocacy organization, in Gilroy, California.
Many residents in the region work on farms or in factories and have limited access to health
insurance. (Christine Mai-Duc/KFF Health News)
Low-Hanging Fruit
As rising healthcare costs have driven up spending by public insurance programs and put pressure on state budgets, states have taken more of a lead in tackling affordability. But they are limited in what they can do. While California has led on prescription drug price transparency and negotiating more competitive marketplace plan rates, it lags other states in some respects, said Sabrina Corlette, a co-director of the Center on Health Insurance Reforms at Georgetown University.
“There’s a lot more they could do to rein in underlying drivers of healthcare costs,” she said of state policymakers.
Some states, for instance, have banned certain facility fees, which allow hospitals to charge higher prices than unaffiliated doctors’ offices even when services are rendered at outpatient clinics that they own. Corlette said such fees increase patient costs while incentivizing hospitals to gobble up more clinics and physician practices.
Oregon capped the payments its public employee health plans make to hospitals, reducing patients’ out-of-pocket spending on outpatient procedures by nearly 10%. Rhode Island limits hospital cost growth through an annual rate review of state-regulated health plans. California has done neither.
California healthcare advocates and researchers say there’s plenty of low-hanging policy fruit that could bring consumers more immediate relief. Insurers and providers could work to automate notoriously inefficient prior authorization procedures, while lawmakers could mandate shorter insurer response times to prior authorization requests, as New Jersey and Vermont have done.
The legislature could also broaden bans on anticompetitive contracting, much like Connecticut and Texas, or expand on Los Angeles County’s program to purchase and forgive residents’ medical debt.
Heath policy experts say even those relatively modest ideas would be a heavy lift in Sacramento, where the industry spends tens of millions of dollars annually to influence lawmakers and state agencies.
“It’s a big, complicated system, and the money is so gigantic,” said Glenn Melnick, a healthcare economist at the University of Southern California. “At some point, the legislature has to hold the line and say, ‘Look, it is the golden goose, but we’re going to have to feed it a little bit less.’”
KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.